
Breasts (mammary glands)
Mammae
View the breasts (mammary glands) in 3DThe breasts are two prominences located on the upper ventral region of the torso in humans and other primates. Both sexes develop breasts from the same embryological tissues. The relative size and development of the breasts is a major secondary sex distinction between females and males. There is also considerable variation in size between individuals. Permanent breast growth during puberty is caused by estrogens in conjunction with the growth hormone. Female humans are the only mammals that permanently develop breasts at puberty; all other mammals develop their mammary tissue during the latter period of pregnancy.
In females, the breasts contain mammary glands, which produce and secrete milk to feed infants. Subcutaneous fat covers and envelops a network of ducts that converge on the nipple, and these tissues give the breast its distinct size and globular shape. At the ends of the ducts are lobules, or clusters of alveoli, where milk is produced and stored in response to hormonal signals. During pregnancy, the breast responds to a complex interaction of hormones, including estrogens, progesterone, and prolactin, that mediate the completion of its development, namely lobuloalveolar maturation, in preparation of lactation and breastfeeding.
Along with their major function in providing nutrition for infants, breasts can figure prominently in the perception of a woman's body and sexual attractiveness. Breasts, especially the nipples, can be an erogenous zone, and part of sexual activity. Some cultures ascribe social and sexual characteristics to female breasts, and may regard bare breasts in public as immodest or indecent. Breasts can represent fertility, femininity, or abundance. Breasts have been featured in ancient and modern sculpture, art, and photography.
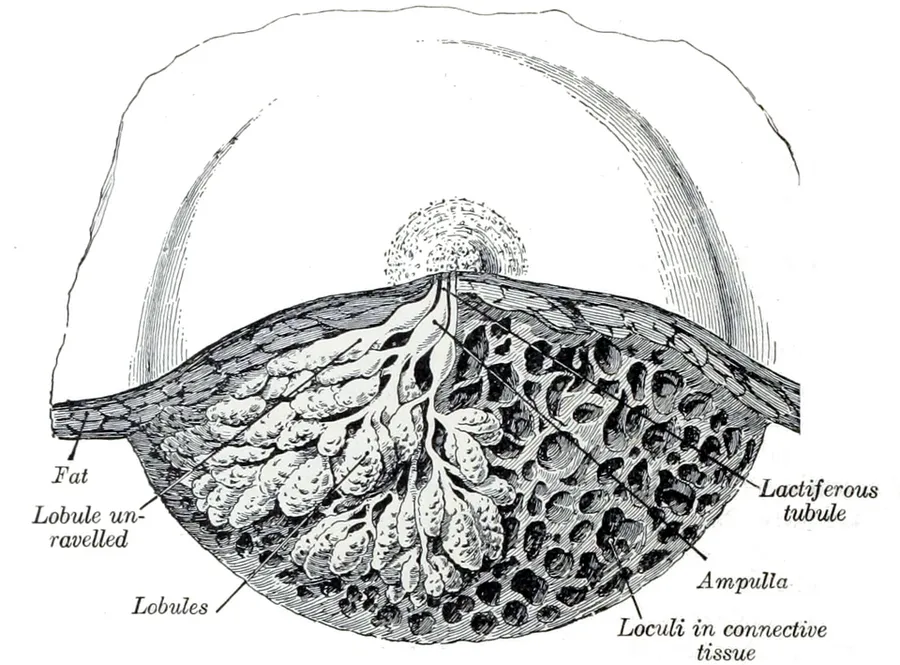
Structure
In women, the breasts overlie the pectoralis major muscles and extend on average from the level of the second rib to the level of the sixth rib in the front of the rib cage; thus, the breasts cover much of the chest area and the chest walls. At the front of the chest, the breast tissue can extend from the clavicle (collarbone) to the middle of the sternum (breastbone). At the sides of the chest, the breast tissue can extend into the axilla (armpit), and can reach as far to the back as the latissimus dorsi muscle, extending from the lower back to the humerus bone (the bone of the upper arm). As a mammary gland, the breast is composed of differing layers of tissue, predominantly two types: adipose tissue; and glandular tissue, which affects the lactation functions of the breasts. The natural resonant frequency of the human breast is about 2 hertz.
Morphologically, the breast is tear-shaped. The superficial tissue layer (superficial fascia) is separated from the skin by 0.5–2.5 cm of subcutaneous fat (adipose tissue). The suspensory Cooper's ligaments are fibrous-tissue prolongations that radiate from the superficial fascia to the skin envelope. The female adult breast contains 14–18 irregular lactiferous lobes that converge at the nipple. The 2.0–4.5 mm milk ducts are immediately surrounded with dense connective tissue that support the glands. Milk exits the breast through the nipple, which is surrounded by a pigmented area of skin called the areola. The size of the areola can vary widely among women. The areola contains modified sweat glands known as Montgomery's glands. These glands secrete oily fluid that lubricate and protect the nipple during breastfeeding. Volatile compounds in these secretions may also serve as an olfactory stimulus for the newborn's appetite.
The dimensions and weight of the breast vary widely among women. A small-to-medium-sized breast weighs 500 grams (1.1 pounds) or less, and a large breast can weigh approximately 750 to 1,000 grams (1.7 to 2.2 pounds) or more. In terms of composition, the breasts are about 80 to 90% stromal tissue (fat and connective tissue), while epithelial or glandular tissue only accounts for about 10 to 20% of the volume of the breasts. The tissue composition ratios of the breast also vary among women. Some women's breasts have a higher proportion of glandular tissue than of adipose or connective tissues. The fat-to-connective-tissue ratio determines the density or firmness of the breast. During a woman's life, her breasts change size, shape, and weight due to hormonal changes during puberty, the menstrual cycle, pregnancy, breastfeeding, and menopause.
Glandular structure
The breast is an apocrine gland that produces the milk used to feed an infant. The nipple of the breast is surrounded by the areola (nipple-areola complex). The areola has many sebaceous glands, and the skin color varies from pink to dark brown. The basic units of the breast are the terminal duct lobular units (TDLUs), which produce the fatty breast milk. They give the breast its offspring-feeding functions as a mammary gland. They are distributed throughout the body of the breast. Approximately two-thirds of the lactiferous tissue is within 30 mm of the base of the nipple. The terminal lactiferous ducts drain the milk from TDLUs into 4–18 lactiferous ducts, which drain to the nipple. The milk-glands-to-fat ratio is 2:1 in a lactating woman, and 1:1 in a non-lactating woman. In addition to the milk glands, the breast is also composed of connective tissues (collagen, elastin), white fat, and the suspensory Cooper's ligaments. Sensation in the breast is provided by the peripheral nervous system innervation by means of the front (anterior) and side (lateral) cutaneous branches of the fourth-, fifth-, and sixth intercostal nerves. The T-4 nerve (Thoracic spinal nerve 4), which innervates the dermatomic area, supplies sensation to the nipple-areola complex.
Lymphatic drainage
Approximately 75% of the lymph from the breast travels to the axillary lymph nodes on the same side of the body, while 25% of the lymph travels to the parasternal nodes (beside the sternum bone). A small amount of remaining lymph travels to the other breast and to the abdominal lymph nodes. The subareolar region has a lymphatic plexus known as the "subareolar plexus of Sappey". The axillary lymph nodes include the pectoral (chest), subscapular (under the scapula), and humeral (humerus-bone area) lymph-node groups, which drain to the central axillary lymph nodes and to the apical axillary lymph nodes. The lymphatic drainage of the breasts is especially relevant to oncology because breast cancer is common to the mammary gland, and cancer cells can metastasize (break away) from a tumor and be dispersed to other parts of the body by means of the lymphatic system.
Morphology
The morphologic variations in the size, shape, volume, tissue density, pectoral locale, and spacing of the breasts determine their natural shape, appearance, and position on a woman's chest. Breast size and other characteristics do not predict the fat-to-milk-gland ratio or the potential for the woman to nurse an infant. The size and the shape of the breasts are influenced by normal-life hormonal changes (thelarche, menstruation, pregnancy, menopause) and medical conditions (e.g. breast hypertrophy). The shape of the breasts is naturally determined by the support of the suspensory Cooper's ligaments, the underlying muscle and bone structures of the chest, and by the skin envelope. The suspensory ligaments sustain the breast from the clavicle (collarbone) and the clavico-pectoral fascia (collarbone and chest) by traversing and encompassing the fat and milk-gland tissues. The breast is positioned, affixed to, and supported upon the chest wall, while its shape is established and maintained by the skin envelope. In most women, one breast is slightly larger than the other. More obvious and persistent asymmetry in breast size occurs in up to 25% of women.
The base of each breast is attached to the chest by the deep fascia over the pectoralis major muscles. The base of the breast is semi-circular, however the shape and position of the breast above the surface is variable. The space between the breast and the pectoralis major muscle, called retromammary space, gives mobility to the breast. The chest (thoracic cavity) progressively slopes outwards from the thoracic inlet (atop the breastbone) and above to the lowest ribs that support the breasts. The inframammary fold (IMF), where the lower portion of the breast meets the chest, is an anatomic feature created by the adherence of the breast skin and the underlying connective tissues of the chest; the IMF is the lower-most extent of the anatomic breast. Normal breast tissue has a texture that feels nodular or granular, with considerable variation from woman to woman.
Breasts have been categorized into four general morphological groups: "flat, spheric, protruded, and drooped", or "small/flat, large/inward, upward, and droopy".
Support
While it is a common belief that breastfeeding causes breasts to sag, researchers have found that a woman's breasts sag due to four key factors: cigarette smoking, number of pregnancies, gravity, and weight loss or gain. Women sometimes wear bras because they mistakenly believe they prevent breasts from sagging as they get older. Physicians, lingerie retailers, teenagers, and adult women used to believe that bras were medically required to support breasts. In a 1952 article in Parents' Magazine, Frank H. Crowell erroneously reported that it was important for teen girls to begin wearing bras early. According to Crowell, this would prevent sagging breasts, stretched blood vessels, and poor circulation later on. This belief was based on the false idea that breasts cannot anatomically support themselves.
Sports bras are sometimes used for cardiovascular exercise, sports bras are designed to secure the breasts closely to the body to prevent movement during high-motion activity such as running. Studies have indicated sports bras which are overly tight may restrict respiratory function.
Development
The breasts are principally composed of adipose, glandular, and connective tissues. Because these tissues have hormone receptors, their sizes and volumes fluctuate according to the hormonal changes particular to thelarche (sprouting of breasts), menstruation (egg production), pregnancy (reproduction), lactation (feeding of offspring), and menopause (end of menstruation).
Puberty
The morphological structure of the human breast is identical in males and females until puberty. For pubescent girls in thelarche (the breast-development stage), the female sex hormones (principally estrogens) in conjunction with growth hormone promote the sprouting, growth, and development of the breasts. During this time, the mammary glands grow in size and volume and begin resting on the chest. These development stages of secondary sex characteristics (breasts, pubic hair, etc.) are illustrated in the five-stage Tanner scale.
During thelarche, the developing breasts are sometimes of unequal size, and usually the left breast is slightly larger. This condition of asymmetry is transitory and statistically normal in female physical and sexual development. Medical conditions can cause overdevelopment (e.g., juvenile breast hypertrophy, macromastia) or underdevelopment (e.g., tuberous breast deformity, micromastia) in girls and women.
Approximately two years after the onset of puberty (a girl's first menstrual cycle), estrogen and growth hormone stimulate the development and growth of the glandular fat and suspensory tissues that compose the breast. This continues for approximately four years until the final shape of the breast (size, volume, density) is established at about the age of 21. Mammoplasia (breast enlargement) in girls begins at puberty, unlike all other primates, in which breasts enlarge only during lactation.
Hormone replacement therapy
Hormone replacement therapy, including gender-affirming hormone therapy, stimulates the growth of glandular and adipose tissue through estrogen supplementation.
In menopausal women, HRT helps restore breast volume and skin elasticity diminished by declining estrogen levels, typically using oral or transdermal estradiol.
In gender-affirming hormone therapy, breast development is induced through feminizing HRT, often combining estrogen with anti-androgens to suppress testosterone. Maximum growth is usually achieved after 2–3 years.
Factors such as age, genetics, and hormone dosage influence outcomes.
Changes during the menstrual cycle
During the menstrual cycle, the breasts are enlarged by premenstrual water retention and temporary growth as influenced by changing hormone levels.
Pregnancy and breastfeeding
The breasts reach full maturity only when a woman's first pregnancy occurs. Changes to the breasts are among the first signs of pregnancy. The breasts become larger, the nipple-areola complex becomes larger and darker, the Montgomery's glands enlarge, and veins sometimes become more visible. Breast tenderness during pregnancy is common, especially during the first trimester. By mid-pregnancy, the breast is physiologically capable of lactation and some women can express colostrum, a form of breast milk.
Pregnancy causes elevated levels of the hormone prolactin, which has a key role in the production of milk. However, milk production is blocked by the hormones progesterone and estrogen until after delivery, when progesterone and estrogen levels plummet.
Menopause
At menopause, breast atrophy occurs. The breasts can decrease in size when the levels of circulating estrogen decline. The adipose tissue and milk glands also begin to wither. The breasts can also become enlarged from adverse side effects of combined oral contraceptive pills. The size of the breasts can also increase and decrease in response to weight fluctuations.
Physical changes to the breasts are often recorded in the stretch marks of the skin envelope; they can serve as historical indicators of the increments and the decrements of the size and volume of a woman's breasts throughout the course of her life.
Breast changes during menopause are sometimes treated with hormone replacement therapy.
Clinical significance
The breast is susceptible to numerous benign and malignant conditions. The most frequent benign conditions are puerperal mastitis, fibrocystic breast changes and mastalgia.
Lactation unrelated to pregnancy is known as galactorrhea. It can be caused by certain drugs (such as antipsychotic medications), extreme physical stress, or endocrine disorders. Lactation in newborns is caused by hormones from the mother that crossed into the baby's bloodstream during pregnancy.
Breast cancer
Breast cancer, which develops from breast tissue, is the most common cause of cancer death among women and a leading cause of general death among women. Factors that appear to be implicated in decreasing the risk of breast cancer are regular breast examinations by health care professionals, regular mammograms, self-examination of breasts, healthy diet, exercise to decrease excess body fat, and breastfeeding.
Signs of breast cancer may include a lump in the breast, a change in breast shape, dimpling of the skin, milk rejection, fluid coming from the nipple, a newly inverted nipple, or a red or scaly patch of skin. In those with distant spread of the disease, there may be bone pain, swollen lymph nodes, shortness of breath, or yellow skin.
Risk factors for developing breast cancer include obesity, a lack of physical exercise, alcohol consumption, hormone replacement therapy during menopause, ionizing radiation, an early age at first menstruation, having children late in life (or not at all), older age, having a prior history of breast cancer, and a family history of breast cancer. About five to ten percent of cases are the result of an inherited genetic predisposition, including BRCA mutations among others. Breast cancer most commonly develops in cells from the lining of milk ducts and the lobules that supply these ducts with milk. Cancers developing from the ducts are known as ductal carcinomas, while those developing from lobules are known as lobular carcinomas. There are more than 18 other sub-types of breast cancer. Some, such as ductal carcinoma in situ, develop from pre-invasive lesions. The diagnosis of breast cancer is confirmed by taking a biopsy of the concerning tissue. Once the diagnosis is made, further tests are carried out to determine if the cancer has spread beyond the breast and which treatments are most likely to be effective.
Male breasts
Both females and males develop breasts from the same embryological tissues. Anatomically, male breasts do not normally contain lobules and acini that are present in females. In rare instances, it is possible for very few lobules to be present; this makes it possible for some men to develop lobular carcinoma of the breast. Normally, males produce lower levels of estrogens and higher levels of androgens, namely testosterone, which suppress the effects of estrogens in developing excessive breast tissue. In boys and men, abnormal breast development is manifested as gynecomastia, the consequence of a biochemical imbalance between the normal levels of estrogen and testosterone in the male body. Around 70% of boys temporarily develop breast tissue during adolescence. The condition usually resolves by itself within two years. When male lactation occurs, it is considered a symptom of a disorder of the pituitary gland.
Plastic surgery
Plastic surgery can be performed to augment or reduce the size of breasts, or to reconstruct the breast in cases of deformative disease, such as breast cancer. Breast augmentation and breast lift (mastopexy) procedures are done only for cosmetic reasons, whereas breast reduction is sometimes medically indicated. In cases where a woman's breasts are severely asymmetrical, surgery can be performed to either enlarge the smaller breast, reduce the size of the larger breast, or both.
Breast augmentation surgery generally does not interfere with future ability to breastfeed. Breast reduction surgery more frequently leads to decreased sensation in the nipple-areola complex, and to low milk supply in women who choose to breastfeed. Implants can interfere with mammography (breast x-ray images).
Source: Wikipedia, The Free Encyclopedia · CC BY-SA 4.0
References
- Breast — Wikipedia, The Free EncyclopediaText from the Wikipedia article "Breast" (CC BY-SA 4.0); excerpted. Licence. Retrieved 2026-10-19. Revision used.
Text above is quoted from the listed sources without changes to its meaning. Image credits and licences are shown with each image. Educational information only, not medical advice.
Related conditions
Educational anatomy reference, not medical advice. About this content.