Pneumothorax (collapsed lung)
Also called: Collapsed lung
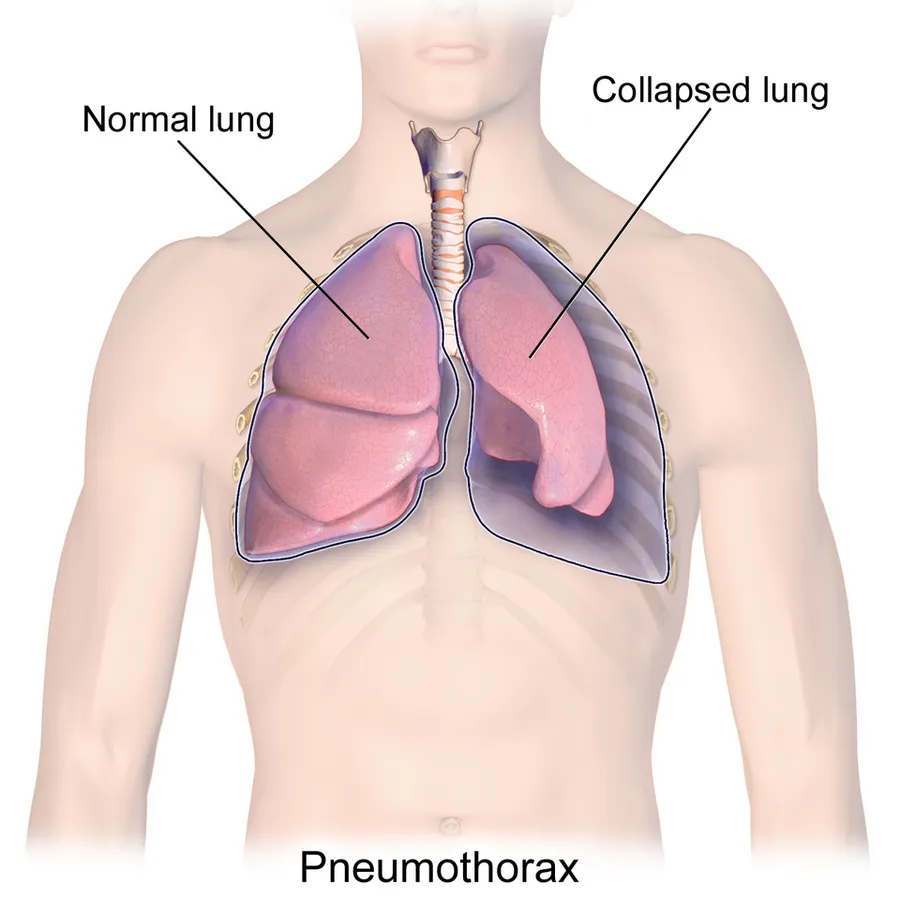
A collapsed lung happens when air enters the pleural space, the area between the lung and the chest wall. If it is a total collapse, it is called pneumothorax. If only part of the lung is affected, it is called atelectasis.
Causes of a collapsed lung include:
- Lung diseases such as pneumonia or lung cancer
- Being on a breathing machine
- Surgery on the chest or abdomen
- A blocked airway
If only a small area of the lung is affected, you may not have symptoms. If a large area is affected, you may feel short of breath and have a rapid heart rate.
A chest x-ray can tell if you have it. Treatment depends on the underlying cause.
NIH: National Heart, Lung, and Blood Institute
Signs and symptoms
A primary spontaneous pneumothorax (PSP) tends to occur in a young adult without underlying lung problems, and usually causes limited symptoms. Chest pain and sometimes mild breathlessness are the usual predominant presenting features. In newborns tachypnea, cyanosis and grunting are the most common presenting symptoms. People who are affected by a PSP are often unaware of the potential danger and may wait several days before seeking medical attention. PSPs more commonly occur during changes in atmospheric pressure, explaining to some extent why episodes of pneumothorax may happen in clusters. It is rare for a PSP to cause a tension pneumothorax.
Secondary spontaneous pneumothoraces (SSPs), by definition, occur in individuals with significant underlying lung disease. Symptoms in SSPs tend to be more severe than in PSPs, as the unaffected lungs are generally unable to replace the loss of function in the affected lungs. Hypoxemia (decreased blood-oxygen levels) is usually present and may be observed as cyanosis (blue discoloration of the lips and skin). Hypercapnia (accumulation of carbon dioxide in the blood) is sometimes encountered; this may cause confusion and – if very severe – may result in comas. The sudden onset of breathlessness in someone with chronic obstructive pulmonary disease (COPD), cystic fibrosis, or other serious lung diseases should therefore prompt investigations to identify the possibility of a pneumothorax.
Traumatic pneumothorax most commonly occurs when the chest wall is pierced, such as when a stab wound or gunshot wound allows air to enter the pleural space, or because some other mechanical injury to the lung compromises the integrity of the involved structures. Traumatic pneumothoraces have been found to occur in up to half of all cases of chest trauma, with only rib fractures being more common in this group. The pneumothorax can be occult (not readily apparent) in half of these cases, but may enlarge – particularly if mechanical ventilation is required. They are also encountered in people already receiving mechanical ventilation for some other reason.
Upon physical examination, breath sounds (heard with a stethoscope) may be diminished on the affected side, partly because air in the pleural space dampens the transmission of sound. Measures of the conduction of vocal vibrations to the surface of the chest may be altered. Percussion of the chest may be perceived as hyperresonant (like a booming drum), and vocal resonance and tactile fremitus can both be noticeably decreased. Importantly, the volume of the pneumothorax may not be well correlated with the intensity of the symptoms experienced by the victim, and physical signs may not be apparent if the pneumothorax is relatively small.
Tension pneumothorax
Tension pneumothorax is generally considered to be present when a pneumothorax (primary spontaneous, secondary spontaneous, or traumatic) leads to significant impairment of respiration and/or blood circulation. This causes a type of circulatory shock, called obstructive shock. Tension pneumothorax tends to occur in clinical situations such as ventilation, resuscitation, trauma, or in people with lung disease. It is a medical emergency and may require immediate treatment without further investigations (see Treatment section).
The most common findings in people with tension pneumothorax are chest pain and respiratory distress, often with an increased heart rate (tachycardia) and rapid breathing (tachypnea) in the initial stages. Other findings may include quieter breath sounds on one side of the chest, low oxygen levels and blood pressure, and displacement of the trachea away from the affected side. Rarely, there may be cyanosis, altered level of consciousness, a hyperresonant percussion note on examination of the affected side with reduced expansion and decreased movement, pain in the epigastrium (upper abdomen), displacement of the apex beat (heart impulse), and resonant sound when tapping the sternum.
Tension pneumothorax may also occur in someone who is receiving mechanical ventilation, in which case it may be difficult to spot as the person is typically receiving sedation; it is often noted because of a sudden deterioration in condition. Recent studies have shown that the development of tension features may not always be as rapid as previously thought. Deviation of the trachea to one side and the presence of raised jugular venous pressure (distended neck veins) are not reliable as clinical signs.
Primary spontaneous
Spontaneous pneumothoraces are divided into two types: primary, which occurs in the absence of known lung disease, and secondary, which occurs in someone with underlying lung disease. The cause of primary spontaneous pneumothorax is unknown, but established risk factors include being of the male sex, smoking, family history of pneumothorax, and a tall, thin build. Smoking either cannabis or tobacco increases the risk. The various suspected underlying mechanisms are discussed below.
Secondary spontaneous
Secondary spontaneous pneumothorax occurs in the setting of a variety of lung diseases. The most common is chronic obstructive pulmonary disease (COPD), which accounts for approximately 70% of cases. The following known lung diseases may significantly increase the risk for pneumothorax.
In children, additional causes include measles, echinococcosis, inhalation of a foreign body, and certain congenital malformations (congenital pulmonary airway malformation and congenital lobar emphysema).
11.5% of people with a spontaneous pneumothorax have a family member who has previously experienced a pneumothorax. Several hereditary conditions – Marfan syndrome, homocystinuria, Ehlers–Danlos syndromes, alpha 1-antitrypsin deficiency (which leads to emphysema), and Birt–Hogg–Dubé syndrome – have all been linked to familial pneumothorax. Generally, these conditions cause other signs and symptoms as well, and pneumothorax is not usually the primary finding. Birt–Hogg–Dubé syndrome is caused by mutations in the FLCN gene (located at chromosome 17p11.2), which encodes a protein named folliculin. FLCN mutations and lung lesions have also been identified in familial cases of pneumothorax where other features of Birt–Hogg–Dubé syndrome are absent. In addition to the genetic associations, the HLA haplotype A2B40 is also a genetic predisposition to PSP.
Traumatic
A traumatic pneumothorax may result from either blunt trauma or penetrating injury to the chest wall. The most common mechanism is the penetration of sharp bony points at a new rib fracture, which damages lung tissue. Traumatic pneumothorax may also be observed in those exposed to blasts, even when there is no apparent injury to the chest.
Traumatic pneumothoraces may be classified as "open" or "closed". In an open pneumothorax, there is a passage from the external environment into the pleural space through the chest wall. When air is drawn into the pleural space through this passageway, it is known as a "sucking chest wound". A closed pneumothorax is when the chest wall remains intact.
Pneumothorax was reported as an adverse event caused by misplaced nasogastric feeding tubes. Avanos Medical's feeding tube placement system, the CORTRAK* 2 EAS, was recalled in May 2022 by the FDA due to adverse events reported, including pneumothorax, leading to 60 injuries and 23 people dying as communicated by the FDA.
Medical procedures, such as inserting a central venous catheter into one of the chest veins or taking biopsy samples from lung tissue, may also lead to pneumothorax. The administration of positive pressure ventilation, either mechanical ventilation or non-invasive ventilation, can result in barotrauma (pressure-related injury) leading to a pneumothorax.
Divers who breathe from an underwater apparatus are supplied with breathing gas at ambient pressure, which results in their lungs containing gas at higher than atmospheric pressure. Divers breathing compressed air (such as when scuba diving) may develop a pneumothorax as a result of barotrauma from ascending just 1 metre (3 ft) while breath-holding with their lungs fully inflated. An additional problem in these cases is that those with other features of decompression sickness are typically treated in a diving chamber with hyperbaric therapy; this can lead to a small pneumothorax rapidly enlarging and causing features of tension.
Newborn infants
Pneumothorax is more common in neonates than in any other age group. The incidence of symptomatic neonatal is estimated to be around 1-3 per 1000 live births. Prematurity, low birth weight and asphyxia are the major risk factors, and a majority of newborn infant cases occur during the first 72 hours of life.
Artificial Pneumothorax
In the late 1800s and early 1900s, physicians namely Carlo Forlanini, a physician from Italy, began experimenting with intentionally collapsing the lungs of patients infected with tuberculosis. The goal of treatment was to deprive the oxygen dependent mycobacterium of the resources it requires to multiply and spread. Although this method fell out of common practice following the advent of pharmaceutical advancements, some research shows that in cases where medications are not effective, AP has successful results. However, the same complications that arise with other mechanisms may still apply, leading to questions of risk vs. benefit.
Diagnosis
The symptoms of pneumothorax can be vague and inconclusive, especially in those with a small PSP; confirmation with medical imaging is usually required. In contrast, tension pneumothorax is a medical emergency and may be treated before imaging – especially if there is severe hypoxia, very low blood pressure, or an impaired level of consciousness. In tension pneumothorax, X-rays are sometimes required if there is doubt about the anatomical location of the pneumothorax.
Chest X-ray
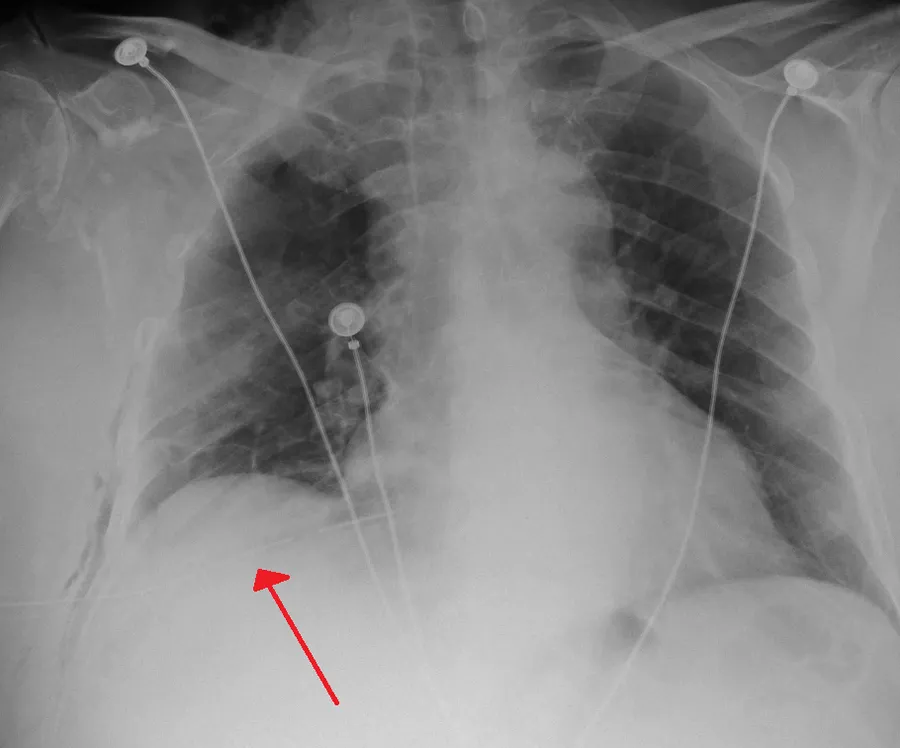
A plain chest radiograph, ideally with the X-ray beams being projected from the back (posteroanterior, or "PA"), and during maximal inspiration (holding one's breath), is the most appropriate first investigation. It is not believed that routinely taking images during expiration would confer any benefit. Still, they may be useful in the detection of a pneumothorax when clinical suspicion is high but yet an inspiratory radiograph appears normal. Also, if the PA X-ray does not show a pneumothorax but there is a strong suspicion of one, lateral X-rays (with beams projecting from the side) may be performed, but this is not routine practice.
It is not unusual for the mediastinum (the structure between the lungs that contains the heart, great blood vessels, and large airways) to be shifted away from the affected lung due to the pressure differences. This is not equivalent to a tension pneumothorax, which is determined mainly by the constellation of symptoms, hypoxia, and shock.
The size of the pneumothorax (i.e. the volume of air in the pleural space) can be determined with a reasonable degree of accuracy by measuring the distance between the chest wall and the lung. This is relevant to treatment, as smaller pneumothoraces may be managed differently. An air rim of 2 cm means that the pneumothorax occupies about 50% of the hemithorax. British professional guidelines have traditionally stated that the measurement should be performed at the level of the hilum (where blood vessels and airways enter the lung) with 2 cm as the cutoff, while American guidelines state that the measurement should be done at the apex (top) of the lung with 3 cm differentiating between a "small" and a "large" pneumothorax. The latter method may overestimate the size of a pneumothorax if it is located mainly at the apex, which is a common occurrence. The various methods correlate poorly but are the best easily available ways of estimating pneumothorax size. CT scanning (see below) can provide a more accurate determination of the size of the pneumothorax, but its routine use in this setting is not recommended.
Not all pneumothoraces are uniform; some only form a pocket of air in a particular place in the chest. Small amounts of fluid may be noted on the chest X-ray (hydropneumothorax); this may be blood (hemopneumothorax). In some cases, the only significant abnormality may be the "deep sulcus sign", in which the normally small space between the chest wall and the diaphragm appears enlarged due to the abnormal presence of fluid.
Computed tomography
A CT scan is not necessary for the diagnosis of pneumothorax, but it can be useful in particular situations. In some lung diseases, especially emphysema, it is possible for abnormal lung areas such as bullae (large air-filled sacs) to have the same appearance as a pneumothorax on chest X-ray, and it may not be safe to apply any treatment before the distinction is made and before the exact location and size of the pneumothorax is determined. In trauma, where it may not be possible to perform an upright film, chest radiography may miss up to a third of pneumothoraces, while CT remains very sensitive.
A further use of CT is in the identification of underlying lung lesions. In presumed primary pneumothorax, it may help to identify blebs or cystic lesions (in anticipation of treatment, see below), and in secondary pneumothorax, it can help to identify most of the causes listed above.
Ultrasound
Ultrasound is commonly used in the evaluation of people who have sustained physical trauma, for example with the FAST protocol. Ultrasound may be more sensitive than chest X-rays in the identification of pneumothorax after blunt trauma to the chest. Ultrasound may also provide a rapid diagnosis in other emergency situations, and allow the quantification of the size of the pneumothorax. Several particular features on ultrasonography of the chest can be used to confirm or exclude the diagnosis.
Treatment
The treatment of pneumothorax depends on a number of factors and may vary from discharge with early follow-up to immediate needle decompression or insertion of a chest tube. Treatment is determined by the severity of symptoms and indicators of acute illness, the presence of underlying lung disease, the estimated size of the pneumothorax on X-ray, and – in some instances – on the personal preference of the person involved.
In traumatic pneumothorax, chest tubes are usually inserted. If mechanical ventilation is required, the risk of tension pneumothorax is greatly increased and the insertion of a chest tube is mandatory. Any open chest wound should be covered with an airtight seal, as it carries a high risk of leading to tension pneumothorax. Ideally, a dressing called the "Asherman seal" should be utilized, as it appears to be more effective than a standard "three-sided" dressing. The Asherman seal is a specially designed device that adheres to the chest wall and, through a valve-like mechanism, allows air to escape but not to enter the chest.
Tension pneumothorax is usually treated with urgent needle decompression. This may be required before transport to the hospital, and can be performed by an emergency medical technician or other trained professional. The needle or cannula is left in place until a chest tube can be inserted. Critical care teams are able to incise the chest to create a larger conduit as performed when placing a chest drain, but without inserting the chest tube. This is called a simple thoracostomy. If tension pneumothorax leads to cardiac arrest, needle decompression or simple thoracostomy is performed as part of resuscitation as it may restore cardiac output.
Conservative
Small spontaneous pneumothoraces do not always require treatment, as they are unlikely to proceed to respiratory failure or tension pneumothorax, and generally resolve spontaneously. This approach is most appropriate if the estimated size of the pneumothorax is small (defined as <50% of the volume of the hemithorax), there is no breathlessness, and there is no underlying lung disease. It may be appropriate to treat a larger PSP conservatively if the symptoms are limited. Admission to hospital is often not required, as long as clear instructions are given to return to hospital if there are worsening symptoms. Further investigations may be performed as an outpatient, at which time X-rays are repeated to confirm improvement, and advice given with regard to preventing recurrence (see below). Estimated rates of resorption are between 1.25% and 2.2% the volume of the cavity per day. This would mean that even a complete pneumothorax would spontaneously resolve over a period of about 6 weeks. There is, however, no high quality evidence comparing conservative to non conservative management.
Secondary pneumothoraces are only treated conservatively if the size is very small (1 cm or less air rim) and there are limited symptoms. Admission to the hospital is usually recommended. Oxygen given at a high flow rate may accelerate resorption as much as fourfold.
Aspiration
In a large PSP (>50%), or in a PSP associated with breathlessness, some guidelines recommend that reducing the size by aspiration is equally effective as the insertion of a chest tube. This involves the administration of local anesthetic and inserting a needle connected to a three-way tap; up to 2.5 liters of air (in adults) are removed. If there has been significant reduction in the size of the pneumothorax on subsequent X-ray, the remainder of the treatment can be conservative. This approach has been shown to be effective in over 50% of cases. Compared to tube drainage, first-line aspiration in PSP reduces the number of people requiring hospital admission, without increasing the risk of complications.
Aspiration may also be considered in secondary pneumothorax of moderate size (air rim 1–2 cm) without breathlessness, with the difference that ongoing observation in hospital is required even after a successful procedure. American professional guidelines state that all large pneumothoraces – even those due to PSP – should be treated with a chest tube. Moderately sized iatrogenic traumatic pneumothoraces (due to medical procedures) may initially be treated with aspiration.
Chest tube
A chest tube (or intercostal drain) is the most definitive initial treatment of a pneumothorax. These are typically inserted in an area under the axilla (armpit) called the "safe triangle", where damage to internal organs can be avoided; this is delineated by a horizontal line at the level of the nipple and two muscles of the chest wall (latissimus dorsi and pectoralis major). Local anesthetic is applied. Two types of tubes may be used. In spontaneous pneumothorax, small-bore (smaller than 14 F, 4.7 mm diameter) tubes may be inserted by the Seldinger technique, and larger tubes do not have an advantage. In traumatic pneumothorax, larger tubes (28 F, 9.3 mm) are used. When chest tubes are placed due to either blunt or penetrating trauma, antibiotics decrease the risks of infectious complications.
Chest tubes are required in PSPs that have not responded to needle aspiration, in large SSPs (>50%), and in cases of tension pneumothorax. They are connected to a one-way valve system that allows air to escape, but not to re-enter, the chest. This may include a bottle with water that functions like a water seal, or a Heimlich valve. They are not normally connected to a negative pressure circuit, as this would result in rapid re-expansion of the lung and a risk of pulmonary edema ("re-expansion pulmonary edema"). The tube is left in place until no air is seen to escape from it for a period of time, and X-rays confirm re-expansion of the lung.
If after 2–4 days there is still evidence of an air leak, various options are available. Negative pressure suction (at low pressures of –10 to –20 cmH2O) at a high flow rate may be attempted, particularly in PSP; it is thought that this may accelerate the healing of the leak. Failing this, surgery may be required, especially in SSP.
Chest tubes are used first-line when pneumothorax occurs in people with AIDS, usually due to underlying pneumocystis pneumonia (PCP), as this condition is associated with prolonged air leakage. Bilateral pneumothorax (pneumothorax on both sides) is relatively common in people with pneumocystis pneumonia, and surgery is often required.
It is possible for a person with a chest tube to be managed in an ambulatory care setting by using a Heimlich valve, although research to demonstrate the equivalence to hospitalization has been of limited quality.
Pleurodesis and surgery
Pleurodesis is a procedure that permanently eliminates the pleural space and attaches the lung to the chest wall. No long-term study (20 years or more) has been performed on its consequences. Good results in the short term are achieved with a thoracotomy (surgical opening of the chest) with identification of any source of air leakage and stapling of blebs followed by pleurectomy (stripping of the pleural lining) of the outer pleural layer and pleural abrasion (scraping of the pleura) of the inner layer. During the healing process, the lung adheres to the chest wall, effectively obliterating the pleural space. Recurrence rates are approximately 1%. Post-thoracotomy pain is relatively common.
A less invasive approach is thoracoscopy, usually in the form of a procedure called video-assisted thoracoscopic surgery (VATS). The results from VATS-based pleural abrasion are slightly worse because they have generally higher recurrence rates than those achieved using thoracotomy in the short term. VATS also produces smaller scars in the skin. Compared to open thoracotomy, VATS offers a shorter in-hospital stays, less need for postoperative pain control, and a reduced risk of lung problems after surgery. VATS may also be used to achieve chemical pleurodesis; this involves insufflation of talc, which activates an inflammatory reaction that causes the lung to adhere to the chest wall.
If a chest tube is already in place, various agents may be instilled through the tube to achieve chemical pleurodesis, such as talc, tetracycline, minocycline or doxycycline. Results of chemical pleurodesis tend to be worse than when using surgical approaches, but talc pleurodesis has been found to have few negative long-term consequences in younger people.
Aftercare
If pneumothorax occurs in a smoker, this is considered an opportunity to emphasize the markedly increased risk of recurrence in those who continue to smoke, and the many benefits of smoking cessation. It may be advisable for someone to remain off work for up to a week after a spontaneous pneumothorax. If the person normally performs heavy manual labor, several weeks may be required. Those who have undergone pleurodesis may need two to three weeks off work to recover.
Air travel is discouraged for up to seven days after complete resolution of a pneumothorax if recurrence does not occur. Underwater diving is considered unsafe after an episode of pneumothorax unless a preventive procedure has been performed. Professional guidelines suggest that pleurectomy be performed on both lungs and that lung function tests and CT scan normalize before diving is resumed. Aircraft pilots may also require assessment for surgery.
Neonatal period
For newborn infants with pneumothorax, different management strategies have been suggested including careful observation, thoracentesis (needle aspiration), or insertion of a chest tube. Needle aspiration may reduce the need for a chest tube, however, the effectiveness and safety of both invasive procedures have not been fully studied.
Prevention
A preventative procedure (thoracotomy or thoracoscopy with pleurodesis) may be recommended after an episode of pneumothorax, with the intention to prevent recurrence. Evidence on the most effective treatment is still conflicting in some areas, and there is variation between treatments available in Europe and the US. Not all episodes of pneumothorax require such interventions; the decision depends largely on estimation of the risk of recurrence. These procedures are often recommended after the occurrence of a second pneumothorax. Surgery may need to be considered if someone has experienced pneumothorax on both sides ("bilateral"), sequential episodes that involve both sides, or if an episode was associated with pregnancy.
Epidemiology
The annual age-adjusted incidence rate (AAIR) of PSP is thought to be three to six times as high in males as in females. Fishman cites AAIR's of 7.4 and 1.2 cases per 100,000 person-years in males and females, respectively. Significantly above-average height is also associated with increased risk of PSP – in people who are at least 76 inches (1.93 meters) tall, the AAIR is about 200 cases per 100,000 person-years. Slim build also seems to increase the risk of PSP.
The risk of contracting a first spontaneous pneumothorax is elevated among male and female smokers by factors of approximately 22 and 9, respectively, compared to matched non-smokers of the same sex. Individuals who smoke at higher intensity are at higher risk, with a "greater-than-linear" effect; men who smoke 10 cigarettes per day have an approximate 20-fold increased risk over comparable non-smokers, while smokers consuming 20 cigarettes per day show an estimated 100-fold increase in risk.
In secondary spontaneous pneumothorax, the estimated annual AAIR is 6.3 and 2.0 cases per 100,000 person-years for males and females, respectively, with the risk of recurrence depending on the presence and severity of any underlying lung disease. Once a second episode has occurred, there is a high likelihood of subsequent further episodes. The incidence in children has not been well studied, but is estimated to be between 5 and 10 cases per 100,000 person-years.
Death from pneumothorax is very uncommon (except in tension pneumothoraces). British statistics show an annual mortality rate of 1.26 and 0.62 deaths per million person-years in men and women, respectively. A significantly increased risk of death is seen in older people and in those with secondary pneumothoraces, when the lung collapses due to another underlying health condition such as chronic lung disease.
Source: Wikipedia, The Free Encyclopedia · CC BY-SA 4.0
References
- Collapsed Lung — MedlinePlus, U.S. National Library of MedicineSource: MedlinePlus, National Library of Medicine Public domain (U.S. government work). Retrieved 2026-10-19.
- Pneumothorax — Wikipedia, The Free EncyclopediaText from the Wikipedia article "Pneumothorax" (CC BY-SA 4.0); excerpted. Licence. Retrieved 2026-10-19. Revision used.
Text above is quoted from the listed sources without changes to its meaning. Image credits and licences are shown with each image. Educational information only, not medical advice.
Related conditions
Educational overview, not medical advice. Treatment varies by person and location. Consult a qualified health professional for diagnosis or care. Content and model notes · Privacy information